Breaking Down Silos Between Acute and Community Care
Updated: Jul 12

Integrated Care Systems are designed to bring organisations together.
At a structural level, that ambition is clear. Acute, community, primary care and social care services are now part of the same system, working towards shared outcomes.
But in practice, silos still exist.
Acute and community services often operate on different systems, with different processes and different operational priorities. Even where relationships are strong, the supporting data and workflows are not always aligned.
This creates friction across patient pathways.
Referrals are not always seamless. Information does not flow consistently between settings. Visibility is limited at the points where coordination matters most.
The impact is felt every day:
Delays in moving patients between services
Duplication of effort across teams
Gaps in clinical visibility during transitions of care
Disjointed patient experiences across the pathway
This is a common challenge in NHS interoperability.
Organisational alignment on its own does not remove silos. What matters is how systems, data and workflows are connected in practice.
Breaking down these silos is less about structure and more about integration.
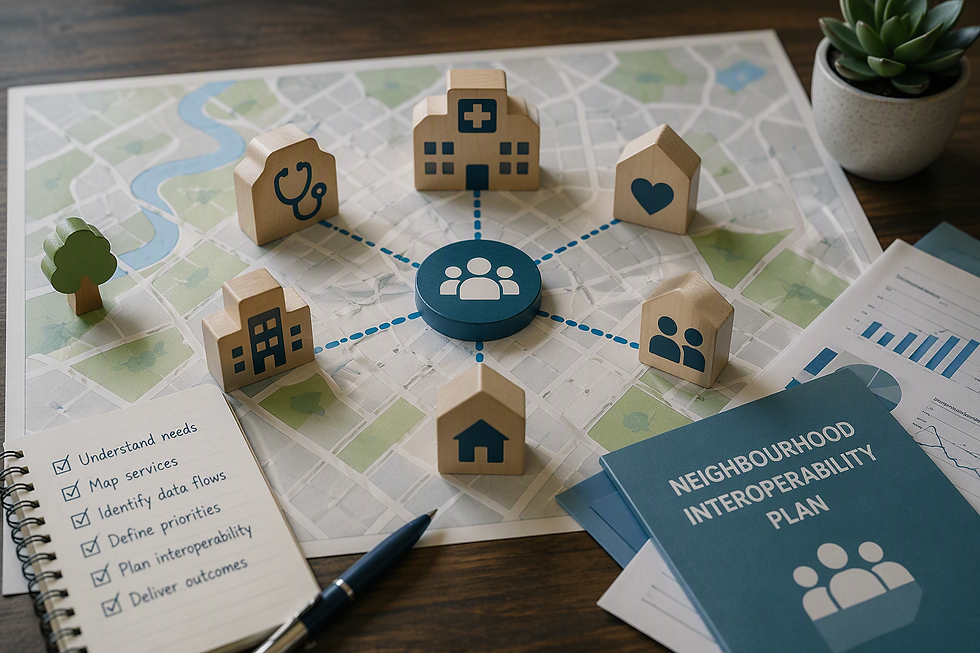
It requires a focus on the pathway itself — how patients move between acute and community services, how information is handed over and how teams coordinate around shared responsibility for care.
That means:
Connecting the systems that support each stage of the pathway
Ensuring that data flows in both directions, not just from one setting to another
Making key information available at transition points such as admission, referral and discharge
Supporting clinicians with timely access to shared data through simple, user-facing interfaces
This is where interoperability becomes meaningful.
Rather than trying to connect everything at once, targeted, pathway-focused integration can address the specific points where coordination breaks down.
These are often well understood. Delayed discharges, incomplete referrals and lack of visibility across services are not new problems. But they persist when integration does not fully support the way teams work.
Making interoperability work in practice means focusing on these moments.
Connecting the right systems, enabling real-time or near real-time data flow where it matters and ensuring that each part of the pathway can see and respond to what the other is doing.
These are not large, abstract challenges. They are practical opportunities to improve how care is delivered across organisational boundaries.
Because ultimately, integrated care is not defined by structure. It is defined by how well services work together for the patient.
And that depends on how effectively information flows between them.
At Osprey, we know that breaking down silos between acute and community care is about much more than connecting systems. It is about enabling information to flow seamlessly across the patient journey, so that every team involved has the visibility they need to make informed decisions and coordinate care effectively.
Drawing on experience from hundreds of NHS interoperability projects, we help organisations design and deliver the integrations that support real care pathways, connecting acute, community, primary care and wider partners in a way that is practical, sustainable and focused on improving outcomes. Because true integrated care depends on more than organisational structures, it depends on information moving where it is needed, when it is needed.
Related Solution: ICB Shared Data & Connectivity Solutions
Effective care depends on effective information sharing. Discover how Osprey helps organisations improve collaboration through connected data and services.